The publications.
Four intersecting areas — surgical identity, social media in medicine, health equity, and geriatric trauma. Each began as a clinical question and grew into something larger.


Surgical Identity
On who surgeons are — and who gets to be one.
The surgeon has long been imagined as a certain kind of person: white, male, technically brilliant, and not particularly warm. That image has real consequences — for patients who don’t feel seen, for trainees who don’t see themselves, and for the culture of surgery itself.
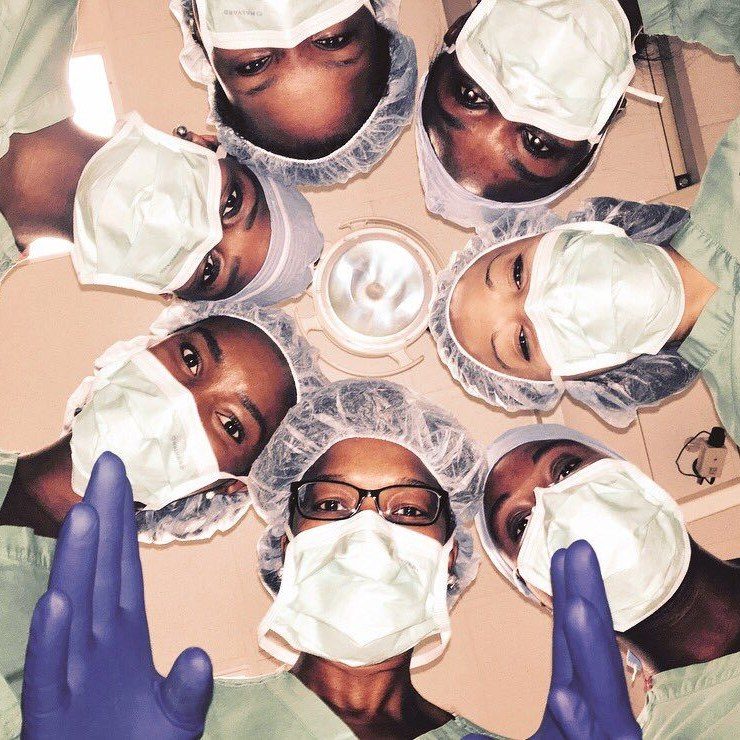
In 2015, I tweeted a single suggestion: what if we used the hashtag #ILookLikeASurgeon? What followed exceeded anything I anticipated — nearly 40,000 tweets, 128 million impressions, and surgeons everywhere showing up as themselves. This work traces the historical roots of surgical stereotypes and documents how social media became a tool for something institutions rarely manage: cultural change at speed.
Selected publications3
-
Ann Surg. 2026. Published online ahead of print. doi: 10.1097/SLA.0000000000007216 · Request a copy
-
#ILookLikeASurgeon: embracing diversity to improve patient outcomes.
BMJ. 2017 Oct 10;359:j4653. doi: 10.1136/bmj.j4653
Key Takeaways
- By 2017 — two years in — #ILookLikeASurgeon had been included in over 150,000 tweets by 35,000 users, generating nearly a billion impressions: proof that a single tweet can reshape a cultural conversation at scale.
- The movement’s implications go beyond representation: a contemporaneous BMJ study found modestly better postoperative outcomes among patients treated by female surgeons. The findings raise important questions about gender, professional expectations, and surgical practice, although the mechanisms underlying these differences remain uncertain.
- The stereotype is not merely inaccurate — it is a professional barrier. Surgeons who don’t fit the white-male mold are less likely to be recognized as surgeons by patients, colleagues, and institutions alike.
- Well-meaning dismissals (“we’re all surgeons,” “only quality matters”) make barriers invisible rather than eliminating them. Naming difference is the first step toward addressing it.
- The goal is not a new singular ideal — it is the end of any singular ideal. Diversity of background, personality, and experience is itself what improves surgical culture and patient care.
-
AMA J Ethics. 2018 May 1;20(5):492–500. doi: 10.1001/journalofethics.2018.20.5.mhst1-1805
Key Takeaways
- The “abrasive white male surgeon” stereotype is not just inaccurate — it actively harms patients who lower their expectations for respectful care, deters medical students from surgical careers, and distorts how colleagues interact with surgeons who don’t fit the mold.
- Women and minorities have been systematically erased from surgical history; the Wikipedia list of 24 “pioneer surgeons” includes not a single woman or person of color — despite their substantial contributions dating back to antiquity.
- #ILookLikeASurgeon, founded by the first author (HJL) with a single tweet in August 2015, generated nearly 40,000 tweets and 128 million impressions within months — proving social media can challenge cultural norms that institutions alone cannot.
- The #NYerORCoverChallenge extended the movement’s reach — and notably, it was often male colleagues leading the photo-taking and sharing, showing that cultural change in surgery requires allies, not only those directly affected.
- The goal was never to help women “believe” they are surgeons. It was to establish that a surgeon can look like anyone.
The goal has never been to help women surgeons believe they are surgeons — but rather to celebrate the diversity of the field and encourage an image of surgeons inclusive of all genders, ethnicities, and personality types.
#ILookLikeASurgeon
2 months
a single tweet
For perhaps the first time, surgeons had a means to put forth images that represent them.
Social Media in Medicine
Research on how Twitter reshaped surgical community and culture.
My interest in how social media shapes communities and conversations in medicine predates #ILookLikeASurgeon. This work examines how platforms like Twitter have created new forms of connection, education, and advocacy across surgical specialties.
Selected publications9
-
How Twitter has connected the colorectal community.
Tech Coloproctol. 2016;20:805–809. doi: 10.1007/s10151-016-1542-3
Key Takeaways
- Twitter lets colorectal surgeons connect, debate, and collaborate in real time across geographic and institutional boundaries — something traditional journals and conferences cannot.
- The #colorectalsurgery hashtag, launched in 2016, linked 1,200+ accounts and generated 25 million impressions within 16 weeks.
- Twitter enabled the EuroSurg collaborative — a student- and trainee-led research network spanning 100+ European universities — showing its power for multi-site research.
- Hashtag communities can serve patients too: #getyourbellyout worked to destigmatize IBD and stomas, extending the reach of the surgical community into public health.
- This article itself was coordinated entirely through Twitter direct messaging — the medium modeling the message.
-
Decoding Twitter: Understanding the History, Instruments, and Techniques for Success.
Ann Surg. 2016 Dec;264(6):904–908. doi: 10.1097/SLA.0000000000001824
Key Takeaways
- Social media overcomes the core limits of traditional academic communication: time delays, peer-review gatekeeping, and conference costs that exclude many voices.
- Of 5,000 physician tweets analyzed, only 3% contained unprofessional content — fears about professionalism are largely overstated.
- #ILookLikeASurgeon reached 12,000+ participants, 66,000+ tweets, and 224 million impressions — demonstrating how a hashtag can drive cultural change at scale.
- “The future of surgical discourse lies not within the technology, but rather within us as we generate the content and govern its quality.”
-
History of Social Media in Surgery.
Clin Colon Rectal Surg. 2017 Sep;30(4):233–239. doi: 10.1055/s-0037-1604250
Key Takeaways
- Surgeons’ adoption of Twitter mirrors laparoscopy’s trajectory: initial skepticism, debates about safety and professionalism, then gradual mass adoption driven by demonstrated value.
- Key milestones include the #hcsm tweetchat (2009), the “twimpact factor” linking tweets to citation rates (2011), Altmetrics as a new measure of scholarly impact, and #ILookLikeASurgeon (2015).
- Hashtags and tweetchats legitimized surgeons’ online presence — creating communities of practice, international journal clubs, and research networks where none existed before.
- Twitter has democratized surgical hierarchy: hashtags like #SurgParenting allowed residents to connect with attendings in ways the traditional OR and conference room did not permit.
-
The academic tweet: Twitter as a tool to advance academic surgery.
J Surg Res. 2018 Jun;226:viii–xii. doi: 10.1016/j.jss.2018.03.049
Key Takeaways
- Twitter advances all five core values of the Association for Academic Surgery: inclusion, leadership, innovation, scholarship, and mentorship — making it uniquely aligned with academic medicine’s mission.
- Up to 21% of academic physicians have considered leaving medicine, citing low inclusion and engagement; Twitter actively mitigates these factors by removing barriers of geography, seniority, and affiliation.
- Live conference tweeting and “infodemiology” — using Twitter data for public health research — represent emerging forms of scholarship that traditional metrics don’t yet capture.
- Fewer than half of UK surgical trainees in 2015 identified a mentor; Twitter extends mentorship beyond institutional walls, connecting trainees globally with experienced voices.
-
Closed Facebook™ groups and CME credit: a new format for continuing medical education.
Surg Endosc. 2019 Feb;33(2):587–591. doi: 10.1007/s00464-018-6376-9
Key Takeaways
- This was the first pilot offering CME credit through a closed Facebook group — using the International Hernia Collaboration (IHC), a global surgical community of 5,400+ members, as the test bed.
- Facebook Live sessions generated more than 6× the engagement of typical IHC posts (avg score 259 vs. 40.8) — live interaction dramatically outperformed passive content.
- An average of 1,116 members (20% of the group) tuned into each live session — a reach that would be nearly impossible to match in person.
- Only ~16 members per session claimed CME credit, likely due to account sign-up friction rather than lack of interest — streamlining the interface could unlock far higher participation.
- Shortly after the pilot, the AMA added a new “other activity” category for social media CME — potentially opening the door to broader, platform-native continuing education in surgery.
-
Global Impact of Social Media on Women in Surgery.
Am Surg. 2020 Feb;86(2):152–157. doi: 10.1177/000313482008600236
Key Takeaways
- Women make up only 19% of the surgical workforce despite representing more than half of U.S. medical school enrollees — a gap that social media is uniquely positioned to help close.
- Women in surgical specialties were more likely than men to lack same-gender mentors at their own institutions, but significantly more likely to use social media to build those mentorship relationships across geography and hierarchy.
- #ILookLikeASurgeon generated 128M+ impressions and ~40,000 tweets in its first two months; by 2020 it had been used more than 200,000 times, with ~3,500 tweets and 16 million impressions in the prior month alone.
- The #NYerORCoverChallenge reached 150M+ impressions and ~10,000 participants, with photos from 53+ countries — including countries where women represent less than 1% of surgeons.
- Social media’s potential may extend beyond attraction to retention: collegial relationships formed online are associated with increased physician motivation, job satisfaction, and a sense of belonging within a specialty.
-
Am Surg. 2021 Apr;87(4):520–526. doi: 10.1177/0003134820950680
Key Takeaways
- At the ACS Clinical Congress 2018, 4,386 tweets were posted by 1,023 accounts — but engagement was concentrated: just 19% of tweeters accounted for 80% of retweets.
- @logghemd ranked 4th overall for retweets received (458 retweets from 29 tweets), ahead of the official @amcollsurgeons account — demonstrating the outsized reach of engaged individual voices.
- The strongest independent predictor of retweets was mentioning other tweeters (OR 3.34), followed by including multimedia (OR 1.88), using additional hashtags (OR 1.32), and follower count.
- #ILookLikeASurgeon was the 4th most-used hashtag at the congress — three years after its founding, the movement remained a defining presence in surgical social media culture.
- Practical lesson: engagement beats broadcasting. Mention others, add images, use the right hashtags — and retweet, not just post.
-
Best practices for surgeons’ social media use: statement of the Resident and Associate Society of the American College of Surgeons.
J Am Coll Surg. 2017 Dec;225(6):682–685.e1. doi: 10.1016/j.jamcollsurg.2017.08.023
Key Takeaways
- The first formal consensus statement on social media use from a major surgical organization — establishing professional norms at a moment when physician social media was expanding rapidly but without institutional guidance.
- Addresses the core tensions surgeons face: the desire to engage publicly while protecting patient privacy, maintaining professionalism, and preserving institutional relationships.
- Affirms that social media can advance education, mentorship, research dissemination, and advocacy — and that these benefits are worth the effort of navigating them thoughtfully.
- Written collaboratively by 23 surgeon authors — itself a model of the community-building the document was describing.
-
Twitter usage at Clinical Congress rises markedly over two years.
Bull Am Coll Surg. 2013 Feb;98(2):22–24.
Key Takeaways
- Among the earliest documented analyses of Twitter use at a major surgical conference — written at a moment when physician social media was still widely dismissed as unprofessional or trivial.
- Documented a marked year-over-year increase in conference tweeting, providing early evidence that social media was becoming a meaningful part of surgical professional culture.
- This early scholarship helped establish the legitimacy of studying physician social media as a serious research area within surgery.

Health Equity
Work on bias, self-awareness, and a more equitable medicine.
My interest in health equity and bias in medicine has been a thread running through my career. This work examines how self-awareness and cultural identity can serve as tools to reduce bias in clinical settings — and what it means to build a medical culture that is more just for both patients and providers.
Selected publications1
-
Self-Awareness and Cultural Identity as an Effort to Reduce Bias in Medicine.
J Racial Ethn Health Disparities. 2018 Feb;5(1):34–49. doi: 10.1007/s40615-017-0340-6
When taught in a safe and supportive setting, self-awareness of one’s biases is an essential first step toward providing compassionate and equitable care for all of one’s patients, regardless of their background.
While most physicians are not explicitly racist or prejudiced, studies show that physicians manifest the same implicit biases and stereotypes found in the general public.
Such cultural competence education as traditionally taught has been criticized for excessively focusing on the culture of the patient, neglecting patient and provider diversity, and decontextualizing social differences.
Key Takeaways
Physician bias is real — and measurable
Providers carry the same implicit biases as the general public. Health disparities driven by provider behavior are well-documented across race, gender, and class.
Focus on the provider, not just the patient
Traditional cultural competency training that centers “other” cultures can reinforce stereotyping. Effective education must interrogate the clinician’s own identity and blind spots.
Cultural identity is multidimensional
Using tools like the cultural genogram, students discovered that their identities — and therefore their biases — cut across race, class, religion, gender, and immigration experience simultaneously.
Equity demands lifelong commitment
The authors favor cultural humility over cultural competence — rejecting the idea of a finite endpoint, and embracing instead a sustained, self-critical practice throughout a career.

Geriatric Trauma
On frailty, age, and outcomes in older trauma patients.
As a resident at the University at Buffalo, I had the privilege of working with trauma and critical care surgeon Dr. Weidun Alan Guo, alongside senior colleagues Joseph L’Huillier, MD, and Kevin Todd, MD. Under Dr. Guo’s mentorship, our work focused on outcomes in geriatric trauma patients, with particular attention to the role of frailty in guiding clinical decision-making.
This collaboration led to papers exploring how frailty shapes outcomes in geriatric trauma — whether in decisions around transfusion, how we define “geriatric” in high-acuity settings, or what actually predicts recovery after rib fractures. Being part of this work sharpened how I think at the intersection of clinical judgment and data, and reinforced my interest in caring for patients whose risk is often more nuanced than age alone suggests.

Selected publications3
-
Transfusion futility thresholds and mortality in geriatric trauma: Does frailty matter?
Am J Surg. 2024 Feb;228:113–121. doi: 10.1016/j.amjsurg.2023.08.020
Key Findings
- Geriatric patients (≥65) reach transfusion futility earlier than younger adults — at 34 units of pRBCs versus 39 units.
- In-hospital mortality was significantly higher in geriatric patients: 63.1% versus 45.8%.
- Frailty status did not significantly shift the transfusion threshold within the geriatric group — the lower threshold held regardless of frailty level.
- Counterintuitively, non-frail geriatric patients had the highest mortality (69.4%) among geriatric subgroups, possibly reflecting a higher injury burden at presentation.
-
The Magic Number 63 — Redefining the Geriatric Age for Massive Transfusion in Trauma.
J Surg Res. 2024 Jul 1;301:205–214. doi: 10.1016/j.jss.2024.04.089
Key Findings
- In this cohort, 63 years was the age cutoff at which differences in massive-transfusion futility thresholds between older and younger patients became statistically significant (34 vs. 40 units, p = 0.04) — challenging the conventional use of 65 in trauma research.
- Despite having less severe injuries and better GCS scores, patients ≥63 had substantially worse outcomes: 61.7% versus 45.4% in-hospital mortality.
- Only 7% of “geriatric” patients were discharged home, compared to 35% of younger patients — underscoring the downstream burden of age in trauma recovery.
-
Age or frailty: What predicts outcomes in geriatric patients with rib fractures?
J Surg Res. 2026 May;321:173–185. doi: 10.1016/j.jss.2026.02.026
Key Findings
- In 203,131 geriatric patients with rib fractures, both age and frailty were independently associated with increased mortality — age is not a proxy for frailty.
- High frailty was the stronger predictor (OR 1.806) compared to advanced age alone (OR 1.379).
- High frailty correlated with longer hospital stays, higher ICU admission rates, and more frequent discharge to skilled nursing facilities.
- Improving outcomes requires attention to both chronological and physiological age — neither alone tells the full story.
Find me elsewhere